Friday, 9 November 2012

War and Peace

I've been musing a bit about life and death, luck and fate.


I'm so lucky to have lived my whole life so far in a time of peace. All the warfare I have seen has been remote, over there, on foreign soil. During my lifetime, these fifty years or so of extended calm, medicine and surgery and the organisation of healthcare have advanced to the point where my tumour could be removed and my life saved, with relative ease.

And I'm so lucky to live in a country where the miracles of modern medicine are accessible to people like me. Reading reams of papers about the management of cancer, I have had to remember that survival rates are affected by the place of treatment as well as the time. For example, many USA studies have poor prognoses because individuals' health insurance don't cover the surgery.

By chance I happened across a Radio 4 programme the other day, "Return to Oasis" http://www.bbc.co.uk/programmes/b01nkt28 about poems from WWII. As we approach Armistice Day it seemed appropriate to share a couple of the poems. I'd give my eye's teeth to be able to write half as feelingly or eloquently. I've transcribed them from the radio broadcast, and any wrong emphasis or phrasing due to punctuation is down to me.

The first is by Wing Commander Dennis McHarrie. I'm intrigued by the line "He fought because he had to fight". Does he mean because of conscription, or morally? But mostly I thought the bitterness, the anger against the sentimentality of non-combatants, rang true. I imagine the Wing Commander saw many good men die.

The second is by Sidney Keys, who died in Tunisia in 1943 shortly before his 21st birthday. He was already a published and respected poet. His imagery is eloquent and brutal, and he had no illusions about the costs of warfare. Had he have lived, he would been around 90 now. The same age as my mum.

Luck

I suppose they’ll say his last thoughts were of simple things
Of April back at home, and a late sun on his wings.
Or that he murmured someone's name
As earth reclaimed him, sheathed in flame.
Oh God. Let’s have no more of empty words.
Lip service, ornamenting death.
The worms don’t spare the hero nor can children feed
Upon resounding praises of his deed.
“He died who loved to live” they’ll say
“Unselfishly, so we might have today”
Like Hell. He fought because he had to fight.
He died, that’s all. It was his unlucky night.

Wing Commander Dennis McHarrie
(originally untitled, the poem commemorates a friend of the poet who took up a defective plane and crashed, a plane the Wg Cdr McHarrie could well have flown himself. )


War Poet

I am the man who looked for peace and found
My own eyes barbed.
I am the man who groped for words and found
An arrow in my hand.
I am the builder whose firm walls surround
A slipping land.
When I grow sick or mad
Mock me not nor chain me:
When I reach for the wind
Cast me not down:
Though my face is a burnt book
And a wasted town.

Sidney Keys

Saturday, 3 November 2012

I'm fed up


I'm fed up.

I'm fed up with feeling drained.

I'm fed up with thinking "I feel a bit better today" only to find myself out of breath with the effort of having a shower.

I'm fed up with wanting a rest after making a cup of tea.

I'm fed up with needing a nap most days.

I'm fed up with not being able to make any plans.

I'm fed up with not knowing how long this is going on for.

I'm fed up with having a tiny, annoying cough and not knowing whether to worry about it or not.

I'm fed up with finding out that by the time I've worked out what I want to do, I don't have the energy to do it.

I'm fed up with having my brain shut down halfway through ...whatever.

I'm fed up with feeling so pathetic about being fed up.

I'm fed up.

Wednesday, 24 October 2012

Hats Off to the Radiography Staff

The Radiotherapy has finished now, and although I'm tired, I'm otherwise unscathed. On the outside, at least. My skin has returned to its normal state, thank goodness, and so far there's no sign of radiation pneumonitis, which was a real fear for me a few weeks back.

The way RT works is that I'll carry on cooking on the inside for another 10 days or so, then gradually start to get better. Some of my tiredness it undoubtedly due to the travelling, and that will improve from here on in, but the bit that's due to the cellular damage caused by RT will continue to build. I have some tightness, or soreness,in my lungs and that might get worse, but so far I'm massively better than I thought I would be at this stage.

I wanted to describe what actually happens in an RT session, before I forget, and pay tribute to the staff who make what could be a technical, almost mechanistic process into a relatively pleasant and friendly series of events.

The RT room is laid out a bit like the sanctuary of some weird techno-church, with a wide open space for the radiographers (the Chosen Ones) to do their ritual tasks, an obsidian altar block, and a massive Shiny-White piece of kit which communes with the God of radioactivity. The sacrificial goat (me) lies on the block which floats up and along into the maw of the Shiny-White, just beneath a large horizontal circular disc about two feet in diameter. The disk is Shiny-White on the top but gunmetal inside glass from below. There's a square area in the centre with 2 combs of lead shielding inside, the teeth of which pull back to reveal The Shape.

Varian RapidArc
Shiny White


The Shape is an extraordinary mystical construct created at the most rarefied levels of the Shiny-White priesthood. Aeons ago, High Planners and Planneresses would spend many days crouched over their sacred tomes and esoteric texts before consulting actual goat bones, but today the Planners apply computerised tomography to virtual goats. They have to ensure that the iso-dose curves created by the accumulation of Shapes is high enough to appease the Shiny-White without killing the goat. This takes many years of study.

The Shapes, once divined, are passed to the Chosen Ones. They in turn, ensure the correct Shapes are applied to the correct goat.

The Chosen Ones, in their blue robes, consult The Book (which looks to the goat like a white lever arch file). The Book rests on the goat's legs and contains sacred runes which must be decoded to ensure the goat's alignment will be pleasing to Shiny-White. As they study the sacred text the Chosen Ones begin their strange and haunting chants: "standard AML", "half a centimetre sup", "1.3 ant and inf" "I've got 91.6" whilst moving the goat into the correct position as dictated by Shiny-White. Occasionally a more junior acolyte (in virginal white) is inducted into the Mysteries, under the beneficient guidance of the Chosen Ones.

Once the goat is positioned to the satisfaction of the Chosen Ones, there are still further final ritual adjustments: 3.2 to the left and 11.6 towards Shiny-White.

Then the Chosen Ones retreat to the vestry. The goat is alone in the room. Shiny-White emits a low humming sound as the disc begins to rotate in a vertical plane about the altar. At some pre-determined point, the humming stops to be replaced by a whirr as a Shape is made in the lead shields. Then another noise: something between a buzz and a beep. This can be momentary, or can last several seconds. When it goes above 10 seconds an alarming clicking noise joins in with the buzz-beep sound. Then buzz/beep stops, and with a whirr the Shape is changed: another hum and Shiny-White moves to a new station, and another buzz-beep. For me, there were 4 angel rays (sorry, angled rays) each time.

Grumpy Old Goat
To the goat, nothing seems to have been achieved by all of this. Nevertheless, the Chosen Ones emerge from the vestry seeming delighted. "Well done" they'd say "you're doing really well" and although the goat is a grumpy old goat thinking, "actually, I haven't done anything at all except lie here" still, the goat is pleased. The altar floats back to its original position and the goat is freed.

Despite the ritual being performed correctly, still Shiny-White is not appeased. More goats must be brought forth, and more, and yet more.

Sometimes the ritual is prefaced by the Taking of the Pictures. "We're going to Take the Pictures today" one of the Chosen Ones will announce. This is allegedly a weekly process, but in practice occurs far more frequently, sometimes happening as often as 4 times in one week. Extra fittings emerge from Shiny-White: two small oblong ears and a huge white square, all of which join in a stately circumnavigation of the head of the goat. Usually, that's it. No change to the aural landscape, just the normal hum. No flashes or lights or strobe effects - frankly, it's all a bit dull. But just once in a while the Taking of the Pictures results in rearranging the goat into a position marginally more pleasing to Shiny-White.

The Vestry

The Chosen Ones spend all day, every day, trying to appease Shiny-White by arranging goats on slabs. It's tough work. Shiny-White requires a constant supply of goats, meaning there are no gaps. So any rearranging of goats, or technical problems, delays, administrative foul ups, late goats, or fools asking dumb questions as I was prone to do, results in prolonging the session so that the ritual continues for an hour or more beyond the scheduled running time.

Despite this the radiographers have been a remarkable pleasant and engaging bunch. Always friendly and supportive, never apparently rushed, and seemingly happy to answer my damn fool questions even though these were prolonging the daily grind. They have clearly found their true calling. I take my hat off to them.

Thursday, 11 October 2012

Memories of British Rail

Thursday. Less than a week to go. Seems like a long, long time.

British Rail Sandwich

I feel like an old fashioned British Rail sandwich. Curling up on myself. I wake up in the night and find I've gone into a tight foetal ball. When I force my legs to stretch out, my knees and ankles click, and I think that I've been locked into that protective position for far too long.

I know I should be thinking up and out and tall and elegant, like the AT teacher I am, but I don't have the energy. I'm scrunched, and round, and small and tired. My feet drag when I walk, and I measure my passage across Liverpool St Station by tiny little landmarks. Just get to the ticket barrier. Just get to the information booth. Not far to the steps. Now to the tube entrance. Just up these stairs. Now down. Find somewhere to lean. Wait for the tube.

I'm weary.

Sadly, not sleepy though. At night, when I try and uncurl myself in bed (I lie on my stomach to flatten myself out, as if I were a piece of carpet that's been rolled up too long) my thoughts start rattling around inside my head like ballbearings in a pinball machine: never going anywhere new and never resting anywhere long enough for me to make sense of them.

Years ago when I was young and stupid we lived in Clapton. I commuted through Liverpool St Station every day. In those days station managers used to play marching music during the morning rush hour (like "The British Grenadiers" or "Colonel Bogey" or "God Bless the Prince of Wales") and the game was to try to not walk in time with the music.

Liverpool Street Station

But the best bit about Liverpool Street in those days was the holes in the roof. Such fun! You got to know where they were along the platform. On a showery day, you could stand confidently beside a roof hole knowing that some newbee would stand next to you thinking you knew where the carriage doors would be: then when the rain came pouring through the hole the newbee would get all wet! Tee Hee! Or better yet, stand right under them on cold winter evenings and the soft, beautiful, gentle snow would fall on you and you alone: it felt like being kissed by angels.

The roof has all been fixed now, and I'll be fixed soon.


Wednesday, 3 October 2012

Half Way There Day

I'm half way there! Oh joy.

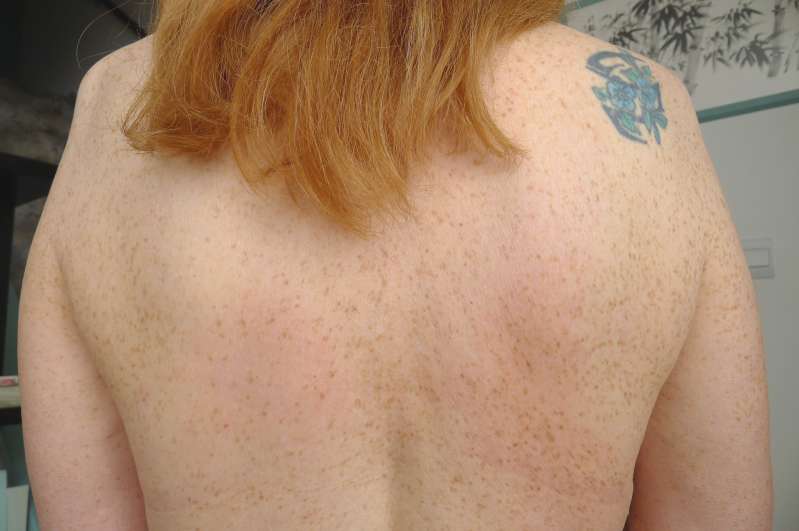
This blog is all about my skin care during RT.

I'm a ginger, so also fair skinned, meaning liable to burn easily. So when the RT Planning session took place and I was warned about the possibility of radiation burns, I took the advice I was given seriously.

I was told to use aqueous cream in place of soap, and as a barrier cream and moisturiser, starting a few days before the treatment and carrying on until a few weeks post treatment. So that's what I did. I hate the stuff, don't feel clean and don't actually think it's a very good moisturiser. Still, at least it doesn't have any nasty chemicals or perfumes which will irritate my skin.

Radiation-induced Eczema: 26/9/2012
Two weeks into treatment and I start to get red, itchy patches on my boobs (where the radiation beams go in) and on my back, diagonally opposite (where the radiation beams come out again). The radiologists think it's probably the first signs of burning. Their advice is, store the aqueous cream in the fridge so it's more cooling, and use it more often. Which I do.

At my next weekly meeting with the oncologists - Dr Carnell herself doesn't come to these, I'm under the TLC of her registrar, Dr Ball (which suits me fine) - I show & tell. The redness has spread to new areas, but not got redder: it's itchy when I use the cream, and it's popped up in one or two places that aren't being irradiated.

The pattern no longer fits in neatly with the radiation beams. Also, the marks aren't getting more intense but instead are spreading out. I think it's eczema. Radiation induced, maybe. Stress related, certainly. I tell Dr Ball what I think.

Dr Ball thinks it's radiation burns. He does however take seriously my comments that the aqueous cream makes my skin itch, and prescribes Diprobase which some patients tolerate better. I try it. It still stings, but less so than the aqueous cream, and still doesn't moisturise very well.

Over the weekend I begin to wonder, why is aqueous cream pushed so strongly when the doctors are clearly aware that some patients can't tolerate it? What is the aqueous cream for, exactly? Would any skin cream do, so long as it's non-irritant? So I start googling.

Many US hospitals do not recommend using aqueous cream during RT, but most UK hospitals seem to think it's good and recommend it for all patients. But however hard I look, I can't find any specific reason to use this particular formulation of skin cream: the criteria seems to be simply about keeping the skin flexible and moist and avoiding irritation.

I'm not a normal patient, I don't have normal skin. 30 years of eczema, and 30 years of all kinds of skin cream, have left me with a sensitive skin. I used aqueous cream briefly and on medical advice back in the 1980's:  it stung then and it stings now.
 
Spreading ??? -induced eczema? : 01/10/2012

More googling, and lo and behold, according to a study by Tsang & Guy published in the British Journal of Dermatology, "the application of Aqueous Cream BP, containing ∼1% SLS, reduced the SC thickness of healthy skin and increased its permeability to water loss. These observations call into question the continued use of this emollient on the already compromised barrier of eczematous skin."
Effect of Aqueous Cream BP on human stratum corneum: abstract

SC, the stratum corneum, is the surface layer of the skin. It consists of dead cells (corneocytes) that lack nuclei and organelles. The purpose of the stratum corneum is to form a barrier to protect underlying tissue from infection, dehydration, chemicals and mechanical stress.

Thinning this layer during RT seems like a seriously bad idea, to me.

Aqueous cream also increases the rate of trans epidural water loss. Not a good idea when one of the criteria for using a moisturiser is to .....the clue is right there in the name.

So now I've stopped using the stuff. I'm putting hydrocortisone cream on the eczema patches and using my normal Dove soap and moisturiser, and the itching has gone away and the redness is starting to recede. As a result I'm more comfortable and relaxed, sleeping better and having fewer nightmares.

When I told the radiography staff I'd stopped the aqueous cream, I got met with concerned frowns. "We recommend that for all our patients" I was told."Yes I know" I replied, "and so do most NHS hospitals. Nevertheless, my skin can't tolerate it, so I'm stopping using it." "You'll have to see the nurse, and show her the cream you're using instead. It's important that it doesn't contain any metals."

So I did, and she was fine about it (although she did suggest going to the Dove Sensitive range rather than the normal stuff). She said, " A lot of our patients can't tolerate the aqueous cream, I don't know why..." I showed her the Tsang and Guy research and she seemed interested. Hopefully, she'll take notice and reconsider the departmental policy to at least tell patients that there are other options.

There's a lovely little research project in there somewhere, for some enterprising nurse or radiographer wanting to make life easier for those of us with sensitive skin.

Postscript: Wednesday 17th October 2012

The skin erythema has largely subsided even though this is at the end of my 5½ weeks of radiotherapy. The skin reaction was not solely down to radiation but due to the effects of the aqueous cream dehydrating and thinning my skin, making it more vulnerable to the radiation.
As soon as I stopped using it, the inflammation started to subside.

17/10/2012: Skin improving after stopping recommended aqueous cream


Friday, 14 September 2012

In Trouble Again

It's Friday. I've calmed down somewhat from the stress of earlier in the week, and I'm getting used to the routine. I turn up, wait in the big waiting room, then the radiographer (who always introduce themselves, first name terms, which is nice: Kathryn or Pira or Claire or Colin or...) take me through to the little waiting area. Then it's through the double doors, round the bendy corridor to the RT machine. Kit off, on couch, some realingment of me on the couch then ZAP!!


But on Friday I went through the bendy corridor to the RT machine and saw two people I'd never met before (a man and a young woman) standing in a corner. She was doing stuff, while he watched. I waited.

After a moment, the radiographer said, "Are you all right Carol?"

I replied, "I'm sorry, I just don't like getting undressed in front of people who haven't introduced themselves."

I got sent to the naughty room.

Of course I didn't. The radiographer introduced them immediately, I got my kit off... all continued as normal.

But it was interesting to note that the 2 newbies were a student radiographer and her male trainer. What? Courtesy and respect weren't part of that module?

Wednesday, 12 September 2012

Trust Me I'm a Doctor: Part 1

I was stressed going in Monday morning, 10th September.  Partly because I was on my way to my first radiotherapy session, again: scary. Also because the appointment time had been changed as “Dr Carnell would like a word first”. No-one likes to hear the phrase “The doctor would like to see you” – it’s inherently scary, too. Still, Godfrey and I reasoned that she probably just wanted to apologise after the balls up last week. Dr Carnell’s Registrar Dr Khan plain forgot to let us know the first treatment  the previous Monday had been cancelled, and so we wasted a fraught trip to London to face the unknowns of radiotherapy for nothing.

An apology? What were we thinking? Dr Carnell explained the reason she wanted to see me was that the proposed treatment had been changed.  The only thing she said, to acknowledge the grief we'd been put through, was “I gather you were messed around last week, but I wasn’t here” Hmmm. I always thought that the buck stopped with the Head of the Clinical Firm, and ultimately the actions of any of the staff in the firm lay with the Consultant in charge regardless of whether they were in the vicinity.

When Godfrey and I first met Dr Carnell, around 6 weeks post-surgery, she  said I needed to have the perimeter of my right lung bathed in radiation using IMRT “which is ideal for this kind of situation”. She described in glowing terms (oh yes, pun definitely intended!) the benefits of IMRT over the conventional, conformal radiation and explained how rogue cancer cells could be lurking anywhere where the tumour had touched my lung or chest wall. That’s a big area: from my collar bone down to the base of my ribs, then sweeping out to the right.

She explained that side effects with IMRT are in general, less severe than for conformal radiation. The radiation is beamed at the target areas from thousands of different directions which means they are able to more effectively avoid healthy tissue and vital organs.  The process was well suited to treating concave surface areas such as the interior of the chest wall, and also where there is constant movement.  When I went in for the planning meeting a week or so later, one of the things they did was study my breathing pattern. It all made sense.


Moving on to Monday, at the quick meeting squeezed in immediately before the first treatment, and Dr Carnell explains the real reason for the delay in starting my treatment. In planning the IMRT the physicists had realised that there was a significant risk of something called ‘radiation pneumonitis’ (RP). This is basically an inflammatory process in the lungs which in the worst cases can lead to scarring and fibrosis in both lungs, with people ending up as a “respiratory cripple”.  So instead, my treatment plan had been revised, meaning the planning had to be re-done using conformal radiation: “back to the old-fashioned way.  Any questions?”

“Errr, what is a respiratory cripple? Sounds like something to be avoided”. “Yes” chipped in the RT department nurse, also in the room and up until then, silent. “I’ve seen it, it’s not something you want to have.”
“Which is why we want to change the plan” explained Dr Carnell, pushing the amended consent form towards me.
 “Do you want me to re-sign that?” I asked
 “Doesn’t really matter, I’m a witness” said the nurse, sitting on the treatment couch, observing.
 I was feeling confused, Godfrey sensed an information vacuum.
“What about the side effects? “  he asked.
”About the same” replied Dr Carnell.
“What about the scarring on the heart?”
“About the same.”
“What about the lungs?”
“About the same.”  

Getting information out of this woman was like getting blood out of a stone.

“What about Carol’s oesophagus?”
 “The side effects on the oesophagus might be a bit worse, you might need to avoid firm food for a while.”

“Will it recover?”
 “Oh yes, after a few weeks.”
The nurse chipped in, “In any case, we can treat that. We can give you things to ease the symptoms”.

Godfrey was still puzzled at the change in the modality. Dr Carnell said they'd tried several times with the IMRT approach, but nothing was safe. Conformal radiation seemed to be the best bet. "The optimal solution?" he asked. "Yes."

So I signed, and we waited for the first treatment. As we waited, we tried to take in the salient points of the lightning quick consultation. Godfrey was saying, there’s something wrong, this doesn’t sit right. He sensed a lot of defensiveness. It wasn’t so much what was being said, as what wasn’t being said.  Afterwards, he began to get more and more concerned. “This doesn't make sense” he was saying “Why did we get all this spiel about how IMRT was so much better, only for Dr Cornell to tell us now, at the last possible moment, that you’re going to have the old fashioned treatment?  How can it be that IMRT’s ideal for treating you one day, and now it could virtually kill you? The medical staff must have known this was the intention when they cancelled last weeks’ appointment, why didn’t they say anything earlier? Why bounce us like that? How come Dr Carnell doesn’t take responsibility for not letting us know about the delay in treatment? So what that she wasn’t here, isn’t she responsible for her staff?”

By the time we got home, Godfrey was bouncing off the ceiling with worry and fury. We looked up RP, and ye gods, it definitely is something to be avoided. In essence, your lungs become leathery and fibrotic and can no longer do the oxygen exchange thing. You can reach a point where you can’t breathe at all, and die. It’s irreversible. A small section of lung can be affected initially, then it can spread through that lung and even into the other side. If you don’t die, you’re on oxygen, gasping for breath, unable to walk more than a few yards.


There are 5 grades of RP:
1) Mild dry cough not requiring treatment
2) Cough requiring narcotic cough medicine or breathing difficulties during activity
3) Severe cough not responsive to narcotics and breathing difficulties when resting, intermittent oxygen or steroids may be required
4) Continuous oxygen or assisted ventilation
5) Fatal

I don't want to be unfair to anyone in this blog, but I do want to be true to my emotional state."State" being the operative word. The more we looked into RP, the worse it got. Some of what follows is, with hindsight, a bit blamey, a but harsh. But that is how I was feeling.

Recent thoracic oncology papers state that 5 - 15% of people treated with RT to the chest area get RP: that’s including lung, breast, oesophageal cancer etc. Not all of them get it severely: sometimes it’s just mild breathlessness or a cough, and sometimes when it’s mild it goes away again. The danger of  getting severe RP (Grade 2 or higher) might be an acceptable risk when you have something terminal. But I don’t. Not at the moment, now the thymoma’s been removed. All I have is a few slow growing cells at the end of a minor blood vessel.

RP is caused by the RT: your chances of getting it vary with the total dose, the volume of lung treated, the fraction size and whether or not you receive chemo at the same time. The critical dosage is 45 Gy: I’m to have 50.4. Over a wide area. And, it’s caused just as much by conformal radiation as IMRT.

We’d been worried about the seemingly extensive nature of the IMRT: I get in principle how it would work for a solid tumour, but couldn’t see how it could be used to treat the ‘rind’ as they call it, where the lungs lie against the chest wall, without doing damage to a load of lung tissue. I’d put my worries down to not understanding fully. Now though, it seems I was right: how come I instinctively knew that, but Dr Carnell, with all her qualifications and experience, didn’t?

We began to play back our previous meeting in our minds, and realised that we didn’t really like what we remembered. When I’d asked questions on our first meeting in the Macmillan Centre on the 6th August, she’d said “it’s all very complicated, you need to have studied oncology for 6 or 7 years to understand this stuff.”  I was somewhat taken aback by her seemingly paternalistic and patronising tone. She also pulled me up when I mispronounced a technical word, like I was some hapless medical student. Today, she’d seemed less than open when answering Godfrey’s questions, and not really explained the reasons behind the change in treatment modality. We couldn't understand how the side effects I was now facing from conformal radiation would be "about the same" as before, since one of  the benefits of IMRT was said to be less severe side effects. Dr Carnell hadn’t felt the need to apologise for the anxiety and stress caused by her staff not telling us of the changed start date. She’d seen us alone the first time, this time she’d organised a witness.


There's a feeling you get sometimes, when someone's giving you unexpected news.It's hard to put your finger on: but there's a sense that words are being used in a very particular way, and meanings are shifting. You run the script back through your mind,and everything seems to be correct, yet the sense is you're in trouble. There was something of that going on in the meeting today, a sense of manipulation; a lack of a true connection.

The only outright euphemism I spotted during the meeting was the nurse saying, "we can treat that", for oesophagitis. Yeah,right. So can a crystal healer, or a reflexologist. The question isn't whether it can be treated, but whether it can be cured. But, as Quentin Crisp said, "Euphemisms are not, as many young people think, useless verbiage for that which can and should be said bluntly; they are like secret agents on a delicate mission, they must airily pass by a stinking mess with barely so much as a nod of the head. Euphemisms are unpleasant truths wearing diplomatic cologne."


The fact that I was looking for euphemisms, for things unsaid, for half truths, for unexplored areas, says it all. I was panicking, and confused, and I had lost faith in my doctor.


STOP! I want to withdraw my consent to RT, altogether. I’ll take the risk of the tumour re-growing, thank you very much.